
Definition and Composition
Wire guides are precision-engineered medical wires, typically composed of stainless steel or nickel‑titanium alloys. Their diameters range from 0.01 to 0.04 inches, and they feature hydrophilic coatings that minimize friction, enabling smooth navigation through vesselsThey enable precise vessel entry, lowering risk now
Common Materials (Stainless Steel, Nickel‑Titanium)
Stainless steel wire guides are the backbone of many endovascular systems, prized for their corrosion resistance, high tensile strength, and biocompatibility. Commonly fabricated from 316L or 316LVM grades, these alloys provide a stable substrate for hydrophilic coatings that reduce friction in the bloodstream. The micro‑structure of stainless steel allows precise control of tip flexibility, enabling safe navigation through tortuous vasculature while maintaining the stiffness required for pushability in large‑bore arterial access. Manufacturers routinely electropolish the surface to eliminate microscopic roughness, then apply a thin, uniform hydrophilic layer that enhances torque response and minimizes vessel trauma during catheter advancement.
Nitinol, a nickel‑titanium alloy, offers shape‑memory and superelastic properties that are invaluable for traversing challenging anatomical pathways. Its ability to recover its original shape after deformation allows the guide to maintain a consistent lumen profile, reducing the risk of vessel injury. Nitinol’s elastic modulus is lower than stainless steel, providing a gentler feel against vessel walls while still delivering the stiffness needed for pushability. In low‑stiffness, highly flexible procedures—such as cerebral or peripheral interventions—nitinol guides excel, offering superior torque control and the capacity to negotiate sharp angles without kinking.
Hybrid designs combine the best of both worlds, pairing a nitinol core with a stainless steel outer jacket to balance flexibility and support. This approach allows the guide to adapt to varying vessel diameters while maintaining torque control, a critical feature for complex endovascular navigation. Surface treatments, including plasma cleaning and electropolishing, ensure a uniform hydrophilic layer that reduces friction and enhances torque response. Quality control protocols verify that the final product meets stringent mechanical and biocompatibility standards, guaranteeing reliable performance across a wide range of clinical applications.
Lorem ipsum dolor sit amet consectetur adipiscing elit. Sed do eiusmod tempor incididunt ut labore et dolore magna aliqua

Diameter and Size Specifications
Wire guides are available in a spectrum of diameters that are critical for procedural success. The most common range spans from 0.01 in. (0.254 mm) to 0.04 in. (1.016 mm). Within this band, manufacturers provide incremental sizes in 0.001‑in. (0.0254 mm) steps to allow clinicians to match the exact lumen of catheters, sheaths, and access ports. Standardization bodies such as ISO 11114 and ANSI AAMI T1 define the nominal diameter, wall thickness, and taper for each size, ensuring interchangeability across brands. A 0.018‑in. guidewire, for example, has a 0.010‑in. (0.254 mm) core with a 0.006‑in. (0.152 mm) stainless‑steel shaft, while a 0.035‑in. guidewire may feature a 0.020‑in. (0.508 mm) core and a 0.015‑in. (0.381 mm) outer diameter. The choice of diameter directly influences flexibility, torque response, and the ability to negotiate tortuous anatomy. In addition, many systems offer “micro” guides (≤0.010 in.) for neurovascular and coronary interventions, and “large‑bore” guides (>0.035 in.) for peripheral and transcatheter aortic valve replacement procedures. Accurate sizing is therefore essential for procedural planning, device compatibility, and patient safety. The selection process often involves a trade‑off between torque control and tip softness, with advanced designs incorporating hybrid cores that combine a stiff proximal segment and a compliant distal tip to navigate challenging anatomies while minimizing vessel trauma. Moreover, the FDA requires rigorous biocompatibility testing, including ISO 10993‑1, to confirm that guidewire materials do not elicit adverse tissue responses. e.g.,

Surface Coatings and Hydrophilic Properties
Hydrophilic coatings on wire guides are engineered to dramatically reduce surface friction, thereby enhancing catheter navigation through tortuous vascular pathways. These polymer layers, often composed of polyethylene glycol or polyvinylpyrrolidone, are applied via dip‑coating or spray techniques and subsequently cured to form a thin, uniform film. The coating thickness typically ranges from 1 to 5 µm, providing a balance between lubricity and mechanical integrity. During insertion, the hydrophilic surface attracts bodily fluids, creating a lubricating film that lowers the coefficient of friction to as low as 0.02–0.04, compared to 0.2–0.3 for uncoated metal. This property is critical in reducing vessel wall trauma, minimizing the risk of dissection, and allowing for smoother advancement of both guidewires and over‑the‑wire devices. Moreover, the coatings are designed to be biocompatible, resisting protein adsorption and platelet adhesion, which helps mitigate thrombogenic responses. In addition to the primary lubricating layer, many manufacturers incorporate a secondary anti‑stick layer, such as silicone or fluoropolymer, to further enhance resistance to biofilm formation and to improve the durability of the hydrophilic film under repeated sterilization cycles. Regulatory standards, including ISO 10993 and FDA 510(k) clearance, require rigorous testing of coating adhesion, durability, and biocompatibility. Clinical studies have demonstrated that hydrophilic wire guides achieve faster procedural times, lower radiation exposure, and improved patient comfort compared to non‑hydrophilic counterparts. Future research is focusing on nanostructured coatings that can actively release anti‑inflammatory agents or provide real‑time feedback on coating integrity during use. Additionally, temperature‑responsive coatings that swell or shrink in response to body heat can adjust the wire’s stiffness dynamically, offering clinicians enhanced control during complex interventions. The integration of micro‑patterned surface topographies has also been shown to reduce friction coefficients by up to 30 % compared to flat coatings, without compromising the wire’s flexibility. Finally, the manufacturing process includes a rigorous quality control step where each coated wire undergoes a sliding friction test against a standardized silicone surface, ensuring that the hydrophilic performance meets the specified threshold before release. The hydrophilic layer also serves as a barrier against oxidation, extending the wire’s functional lifespan during repeated use. In high‑pressure angiographic procedures, the reduced friction translates to a lower risk of vessel injury, which is particularly beneficial when navigating calcified or stenotic segments. Moreover, the coating’s hydrophilicity can be tuned by adjusting the polymer blend ratio, allowing manufacturers to customize the wire for specific clinical scenarios such as neurovascular or peripheral interventions. The durability of the coating is verified through accelerated aging tests, where coated wires are subjected to 10,000 cycles of insertion and withdrawal in a saline bath at 37 °C, simulating years of clinical use. The resulting data confirm that the coating retains over 95 % of its lubricity after the test, meeting the stringent requirements set by international regulatory bodies.

Types of Wire Guides in Interventional Radiology
In interventional radiology, wire guides are categorized primarily into navigational and working wires. Navigational wires are designed for vessel selection; they possess a softer, more flexible tip and a lower overall stiffness, allowing the operator to steer through tortuous anatomy with minimal vessel trauma. These wires often feature a hydrophilic surface coating that reduces friction and enhances glide. Working wires, by contrast, provide the necessary support for device delivery. They have a higher distal tip stiffness and a more robust shaft, enabling the operator to advance catheters, balloons, or stents over the guidewire. The transition from a navigational to a working wire is a common procedural step, ensuring both safe access and effective device deployment. Some systems combine both characteristics in a single wire, offering a tapered tip that gradually increases stiffness toward the shaft. This hybrid design allows the operator to maintain precise control during the initial navigation phase while still delivering sufficient support for subsequent device manipulation. The selection of a particular wire type depends on the vascular target, the complexity of the lesion, and the required device profile. Proper choice of wire guide type is therefore essential for procedural success and patient safety.
Common tip configurations include the classic J‑shaped tip, which offers a gentle entry into the arterial system, and the angled tip, which assists in selective catheterization of branch vessels. Some wires incorporate a pre‑curved or “U‑shaped” tip to navigate challenging anatomies such as the aortic arch or the subclavian artery. The shaft may be reinforced with a braided or coiled structure to improve torque response and pushability. In addition, certain wires feature a dual‑layer construction: an inner core of stainless steel for strength and an outer hydrophilic coating for low friction. The outer layer may be further treated with a silicone or polyethylene glycol (PEG) coating to enhance lubricity. These design choices allow interventionalists to tailor the wire’s mechanical properties to the specific demands of each case, balancing flexibility, support, and safety.
In practice, the choice between a navigational and a working wire is guided by the lesion’s location and the required device profile. For coronary interventions, a highly flexible, hydrophilic navigational wire is often paired with a stiff, supportive working wire to achieve rapid device delivery while minimizing vessel trauma!

Guidewire vs Access Wire
Guidewires and access wires are both essential components in interventional procedures, yet they serve distinct purposes and possess unique design characteristics. A guidewire is engineered for navigation and support; it typically features a soft, tapered tip that can be angled or shaped to negotiate tortuous anatomy. Its shaft is often composed of a flexible alloy such as nitinol or stainless steel, providing a balance between pushability and torque control. The hydrophilic coating reduces friction against vessel walls, allowing the wire to glide smoothly during catheter advancement.
An access wire by contrast is primarily a conduit for initial vessel entry. It is usually stiffer and has a robust tip, sometimes with a straight or slightly angled configuration, to facilitate rapid crossing of stenotic lesions or occlusions. Access wires are often used in the first phase of a procedure to establish a stable platform before a delicate guidewire is introduced. While both wires may share similar core materials, the access wire’s surface may be coated with a thicker, durable polymer to withstand higher forces during the initial crossing.
In practice, the choice between a guidewire and an access wire depends on the procedural step and the vascular environment. Interventionalists select an access wire for rapid, forceful entry and then switch to a guidewire for precise navigation, catheter placement, and support of interventional devices. Understanding these distinctions ensures optimal device selection, procedural safety, and successful outcomes.
Guidewire Flexibility and Stiffness
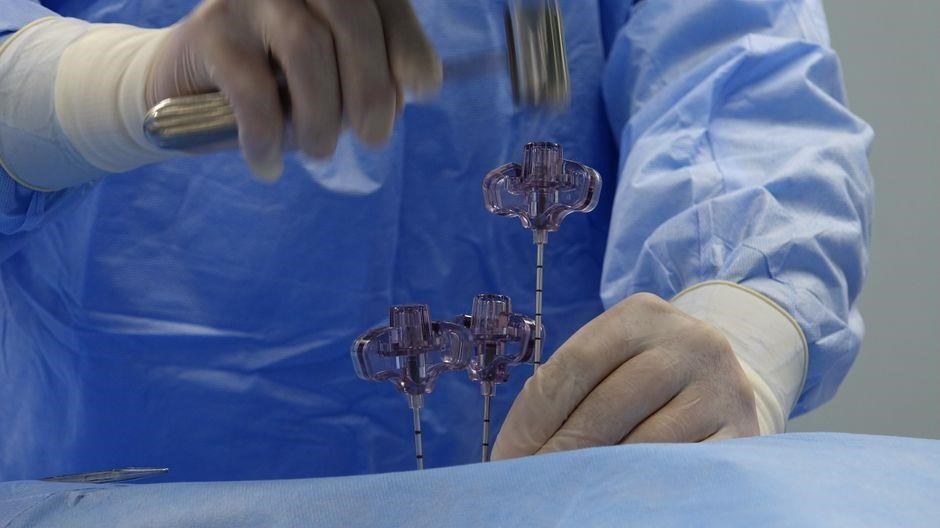
Guidewires are engineered to balance flexibility and stiffness, allowing clinicians to navigate tortuous anatomy while maintaining support for device delivery. The core material—often stainless steel or nickel‑titanium—provides a baseline modulus, but the wire’s overall behavior is tuned through wire diameter, wire construction (single‑core, double‑core, or braided), and surface coatings. A thinner core increases flexibility, enabling gentle passage through narrow or sharply angled vessels, whereas a thicker or reinforced core offers the stiffness required to advance catheters or push through resistant lesions. Hydrophilic coatings reduce friction, further enhancing flexibility by allowing the wire to glide smoothly. Manufacturers also employ variable stiffness designs, such as tapered or segmented constructions, where the distal tip is highly flexible for vessel selection and the proximal segment is stiffer to transmit torque and support larger devices. This dual‑characteristic design is critical in interventional radiology, where precise control and safe navigation are paramount. In practice, clinicians select a guidewire based on the target vessel’s size, tortuosity, and the therapeutic device’s requirements, ensuring optimal balance between maneuverability and pushability.
During device deployment, the guidewire’s stiffness must transmit torque accurately to the distal tip, preventing kinking or buckling. Excessive flexibility can lead to loss of control, while excessive stiffness may cause vessel trauma. Therefore, manufacturers provide a range of tip stiffness options, often labeled as “soft,” “medium,” or “hard,” and may incorporate a hydrophilic coating to mitigate friction. The choice of wire guide is guided by procedural factors such as the need for rapid advancement, the presence of calcified lesions, or the requirement for high‑pressure support. In addition, the wire’s surface roughness and coating integrity are critical for maintaining consistent flexibility over repeated use, as wear can alter the wire’s mechanical properties and compromise safety. Quality control testing, including bend tests, torque measurements, and pull‑out strength assessments, ensures that each wire guide meets the stringent specifications necessary for safe clinical application.
Clinicians rely on these engineered properties to achieve successful outcomes in complex vascular interventions!

Applications in Medical Device Manufacturing
In manufacturing of interventional devices, wire guides serve as the backbone for a variety of components. They are incorporated into catheter assemblies to provide a stable, steerable core that allows the device to be positioned accurately within the vasculature. During the fabrication of stent delivery systems, wire guides are embedded within the delivery catheter to transmit torque and maintain lumen integrity while the stent is expanded. In the production of embolization coils, a wire guide is used as a support shaft that can be withdrawn after the coil has been deployed, ensuring precise placement and reducing the risk of migration. Additionally, wire guides are employed in the assembly of microcatheters for neurointerventional procedures; their fine diameterhigh flexibility enable navigation through tortuous cerebral vessels. The integration of wire guides also facilitates the attachment of imaging contrast agents, as the guide can act as a conduit for contrast delivery during fluoroscopic guidance. Manufacturers often customize the surface coating of wire guides—such as hydrophilic or silicone layers to match the friction profile required for specific device categories, thereby improving pushability and reducing procedural time. This integration ensures seamless device deployment, enhances procedural efficiency, and supports the development of next-generation interventional tools.

Manufacturing Process: From Design to Mass Production
The journey of a wire guide begins with a multidisciplinary team that blends clinical insight and engineering precision. Designers employ advanced CAD tools to model the wire’s tip geometry, shaft taper, and overall length, ensuring seamless compatibility with existing catheters and imaging systems; Material selection—typically stainless steel or nickel‑titanium alloys—balances strength, flexibility, and biocompatibility, while also meeting regulatory standards for medical devices, and ensuring sterility.
Following design, the wire undergoes a drawing process; It is pulled through smaller dies, reducing diameter while preserving core integrity and mechanical properties. Real‑time monitoring of tensile strength and diameter ensures compliance with specifications. Once the base wire reaches the target gauge, a hydrophilic polymer coating—usually polyethylene glycol—is applied via dip‑coating or spray, then cured under temperature at humidity to lock in low‑friction characteristics.
Quality control is integral at every stage. Non‑destructive testing, such as ultrasonic inspection, verifies internal homogeneity, while optical microscopy checks for surface defects. Mechanical testing—including pull‑out, torque, and bend tests—confirms that the wire meets ISO 80369 and ASTM F 2060 standards. Functional validation ensures smooth navigation and tip responsiveness in a simulated vascular environment. Sterilization efficacy is verified through microbiological assays, confirming compliance!!!
In mass production, automated assembly lines perform batch coating, drying, and packaging under ISO 13485‑certified cleanrooms. Each batch receives a unique lot number, and traceability records track every component from raw material to final product. The finished wire guides are sterilized—commonly via ethylene oxide or gamma irradiation and packaged in sterile, sealed containers, ready for distribution to hospitals and suites ensuring recall capability if needed.!!!!!!!!!!!!!!!!!!!!!

Quality Assurance and Testing Standards
Wire guides undergo quality assurance protocols to ensure patient safety and reliability. The process begins with material verification, where stainless steel or nickel‑titanium alloys are tested for purity, strength, and corrosion resistance using testing machines. Next, dimensional inspections confirm that diameters and lengths match specifications, employing micrometers and comparators. Surface coating integrity is evaluated through contact angle measurements and adhesion tests, ensuring the layer remains uniform and durable. Functional performance is assessed by performing torque, bend, and pull‑through tests on vascular models, measuring resistance and flexibility precisely under controlled conditions.
Accelerated aging studies expose wire guides to elevated temperatures and cyclic mechanical loads, verifying that the hydrophilic coating and structural integrity remain intact over projected shelf lives. Electrical impedance spectroscopy detects micro‑cracks or delamination that could compromise performance. The final acceptance criteria are documented in a release checklist, and any deviations trigger root‑cause analysis and corrective actions before release. Post‑market surveillance includes mandatory adverse event reporting and periodic audits to maintain compliance with Good Manufacturing Practice guidelines. These measures ensure that each wire guide meets safety and efficacy daily benchmarks.
The manufacturing facility is subject to ISO 13485 audits, ensuring environmental controls, personnel training, and equipment calibration meet stringent requirements. The quality system incorporates statistical process control charts for key parameters such as wire diameter and coating thickness, enabling real‑time monitoring and early detection of drift. Supplier qualification processes include third‑party testing and on‑site inspections to validate raw material quality. The entire QA workflow is supported by an integrated electronic quality management system that automates documentation, audit trails, and corrective action workflows, thereby reducing human error and enhancing comprehensive traceability.

Common Clinical Uses (e.g., Catheterization, Angiography)
Wire guides are essential in interventional radiology, acting as the foundation for procedures such as coronary angiography, peripheral arterial interventions, and central venous catheter placement. In coronary angiography, a hydrophilic-coated guidewire is advanced through the femoral or radial artery, navigated across stenotic lesions, and positioned distal to the target vessel to allow contrast injection and imaging. The wire’s flexibility and torque control enable operators to negotiate tortuous anatomy while minimizing vessel trauma.
In peripheral interventions, wire guides facilitate balloon angioplasty and stent deployment in iliac, femoral, and popliteal arteries; their tip design—soft, angled, or tapered—provides precise access to branch vessels. For central venous catheterization, a guidewire is first threaded through the puncture site, then a catheter is advanced over the wire into the superior vena cava or jugular vein, ensuring accurate placement and reducing arrhythmia risk.
Wire guides are also employed in endovascular aneurysm repair, guiding stent graft delivery systems to the aortic bifurcation, and in neurointerventional procedures, such as mechanical thrombectomy, where a specialized microguidewire navigates cerebral vessels to reach occlusions. Across all these applications, the wire’s surface coating reduces friction, allowing smoother passage, while its mechanical properties—balance of stiffness for support and softness for safety—are critical for procedural success and patient outcomes. Wire guide design ensures safety efficacy!!.
Future Trends and Innovations in Wire Guide Technology
Emerging developments in wire guide technology are reshaping interventional procedures. Researchers are integrating smart coatings that respond to temperature or pH, enabling real‑time adjustment of hydrophilicity and reducing vessel trauma. Biodegradable polymers, such as poly(lactic‑co‑glycolic acid), are being blended with nickel‑titanium to create guides that safely dissolve after use, eliminating retrieval risks.
Advanced shape‑memory alloys with tunable stiffness allow a single guide to transition from a flexible navigation mode to a rigid support mode, guided by external magnetic fields. Embedded micro‑sensors measure pressure, temperature, and position, transmitting data to handheld consoles for precise navigation and reduced radiation exposure.
3‑D printing of composite guides offers patient‑specific curvature, improving access to tortuous anatomy. Nanostructured surface treatments reduce bacterial adhesion and thrombogenicity, enhancing long‑term safety. Artificial intelligence algorithms interpret sensor data to predict vessel wall interaction, suggesting optimal tip orientation in real time.
Regulatory pathways are evolving to accommodate these innovations, with accelerated approval for devices demonstrating reduced procedural time and complication rates. Collaboration between material scientists, bioengineers, and clinicians will accelerate the transition from prototype to market, promising safer, more efficient interventions.
These breakthroughs promise to cut procedure times by up to 30%inthe.
Leave a Reply
You must be logged in to post a comment.